
Amylin: The Forgotten Pancreatic Hormone Pharma Now Calls the Future of Weight Loss
By Andrea Vidali, MD
Discovered in 1987, abandoned for two decades, and now the most coveted target in obesity drug development — what every clinician needs to know about the amylin renaissance.
Quick Answer
Amylin is a hormone secreted by the pancreas alongside insulin every time you eat. It tells the brain you are full, slows stomach emptying, and blunts glucose spikes. Discovered in 1986–1987 and largely shelved for twenty years, amylin is now the single hottest target in metabolic medicine. Novo Nordisk, Eli Lilly, Roche, Pfizer, and a long list of biotechs are pouring hundreds of millions of dollars into amylin analogs and combination drugs. Early data suggest these drugs can match or exceed Ozempic-class weight loss with a substantially better side-effect profile. The first amylin-based obesity drug, CagriSema, is under FDA review now, with a likely launch this year and a wave of competitors arriving through 2027 and 2028.
What Is Amylin? A 60-Second Primer
Amylin, also known as islet amyloid polypeptide (IAPP), is a 37-amino-acid peptide hormone co-secreted with insulin from the beta cells of the pancreas, in roughly a 1:100 ratio with insulin. After every meal, your pancreas releases both hormones in tandem. Insulin handles glucose disposal.
Amylin handles three jobs that insulin does not:
-
Slows gastric emptying — food leaves the stomach more gradually, smoothing the post-meal glucose curve.
-
Suppresses glucagon — preventing the liver from dumping more glucose into the bloodstream after eating.
-
Activates satiety centers in the brain — specifically in the hindbrain (area postrema) and hypothalamus, telling you to stop eating.
Dr. Vidali notes: In endocrinology we have spent two generations focused almost entirely on insulin. Yet amylin is the second hand on the same metabolic clock. When patients with type 2 diabetes lose beta-cell function, they lose both insulin and amylin. Replacing only insulin is, biologically, half a treatment. The field is finally catching up to that reality — and the implications for obesity, not just diabetes, are enormous.
A Brief History: Discovery, Approval, and Twenty Years in the Wilderness
1986–1987: The Discovery
Amylin was identified independently in 1986 by Per Westermark in Sweden and in 1987 by Garth Cooper and colleagues at the University of Oxford. Both teams were trying to answer a century-old question: what is the strange amyloid material that pathologists kept finding in the pancreases of patients with type 2 diabetes? Eugene Opie had first described those hyaline deposits in 1901. It took 85 years to identify the protein responsible — and it turned out not to be insulin or any of its precursors, but an entirely new beta-cell hormone. That discovery launched Amylin Pharmaceuticals, founded in San Diego in 1987 by Howard Greene Jr., specifically to develop a synthetic analog of the hormone for diabetes.
1992–2005: A Long, Difficult Road
Amylin Pharmaceuticals took its synthetic analog, pramlintide (brand name Symlin), through more than a decade and a half of clinical development. The natural hormone was a nightmare to formulate — it is sticky, aggregation-prone, and forms the very amyloid fibrils that destroy pancreatic beta cells in diabetes. Pramlintide was engineered to keep the appetite and glucose effects while resisting fibril formation. In March 2005 the FDA finally approved Symlin as the first-in-class amylin analog.
Why Amylin Was Then Abandoned
-
Inconvenient dosing — three to four extra mealtime injections on top of insulin.
-
Hypoglycemia risk when combined with mealtime insulin.
-
Nausea and dose-titration complexity in early use.
-
Commercial collapse of the obesity program: in 2011 Amylin and Takeda discontinued the pramlintide/metreleptin combination after a “commercial reassessment” — now widely viewed as one of the most expensive strategic missteps in modern pharma history.
-
The GLP-1 tidal wave: liraglutide, then semaglutide, then tirzepatide, delivered better weight loss with vastly easier dosing.
By 2012, Amylin Pharmaceuticals was acquired by Bristol-Myers Squibb, the obesity pipeline was effectively shelved, and the hormone slid into pharmacological obscurity.
Dr. Vidali notes: The story of amylin is not that the science failed. It is that the delivery technology of the 1990s could not keep up with the biology. We had a brilliant hormone trapped inside a clumsy molecule. Modern peptide engineering — long-acting analogs, fatty-acid conjugation, oral formulations — is now solving exactly the problems that killed amylin the first time.
Why Amylin Is Back — And Why Pharma Is Spending Hundreds of Millions
Three things changed between 2015 and 2025.
First, peptide engineering matured: long-acting amylin analogs that survive in circulation for a week, instead of minutes, are now feasible. Cagrilintide is the proof of concept.
Second, the receptor biology was finally cracked. In August 2025, researchers at the University of Oklahoma published in Science Signaling a structural and functional map of how amylin activates its three brain receptors (calcitonin receptor paired with RAMP1, RAMP2, or RAMP3). Drug developers can now design molecules that hit only the appetite-suppressing receptor subtypes while sparing those associated with nausea and cardiovascular side effects.
Third, the GLP-1 ceiling became visible. Semaglutide and tirzepatide are remarkable, but a meaningful percentage of patients either do not tolerate them or plateau before reaching their goal weight.
Mechanism Comparison: Amylin Analogs vs GLP-1 Receptor Agonists
| Mechanism | GLP-1 agonists (semaglutide, tirzepatide) | Amylin analogs (cagrilintide, eloralintide) |
| Receptor target | GLP-1R (± GIP-R for tirzepatide) | Calcitonin receptor + RAMP1/2/3 complexes |
| Site of action | Pancreatic β-cells, gut, hypothalamus | Area postrema (hindbrain), hypothalamus, gut |
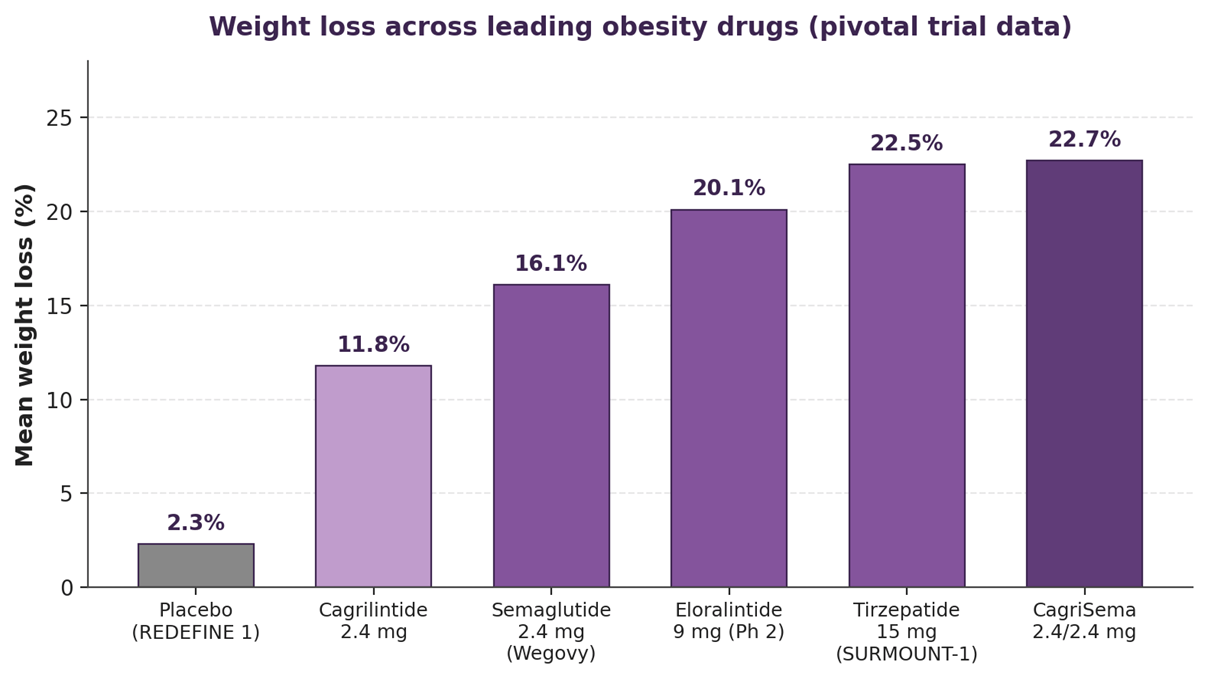
| Typical weight loss | 15–22.5% at 68–72 wk | 11–20% monotherapy; up to 22.7% combined w/ GLP-1 |
| GI tolerability | Notable nausea/vomiting; dose-dependent | Substantially improved profile in Ph 2 head-to-head signals |
| Lean mass preservation | Concern about loss of lean tissue | Preliminary advantage; under further study |
| Combination potential | Backbone of next-gen combos | Highly additive (CagriSema is the proof of concept) |
Head-to-Head: Weight Loss Across Pivotal Trials
The figure below summarizes mean weight loss across the main pivotal trials of GLP-1 agonists and amylin analogs. Eloralintide monotherapy (20.1% at 9 mg, 48 weeks) approaches tirzepatide territory, while CagriSema demonstrates the additive power of dual-mechanism therapy.
Body Composition: Quality of Weight Loss Matters
A landmark prespecified analysis from REDEFINE 1 examined not just the magnitude of weight loss but the composition of tissue lost. CagriSema produced a 35.7% reduction in fat mass with comparatively modest lean-tissue loss — a clinically important distinction for older patients and those at risk of sarcopenia.

The Amylin Pipeline: Who Is Building What
| Drug | Sponsor | Phase / Status | Headline data |
| CagriSema (cagrilintide + semaglutide) | Novo Nordisk | FDA filed Dec 2025 | 22.7% mean weight loss at 68 wk (REDEFINE 1, NEJM 2025) |
| Eloralintide (LY3841136) | Eli Lilly | Phase 3 starting 2026 | 20.1% at 9 mg, 48 wk (Phase 2, Lancet 2025) |
| Petrelintide | Roche / Zealand | Phase 2 | ZUPREME-1 readout H1 2026; mono and combo with CT-388 |
| MET-233i | Pfizer (via Metsera) | Phase 2 | First Phase 2 readouts expected H1 2026 |
| Cagrilintide (mono) | Novo Nordisk | Phase 3 component | 11.8% at 68 wk in REDEFINE 1 |
| Pramlintide (Symlin) | AstraZeneca (legacy) | FDA approved 2005 | First-in-class amylin analog; mealtime injection adjunct to insulin |

Dr. Vidali notes: When five of the largest pharmaceutical companies on earth are simultaneously paying premium prices to acquire amylin assets, that is the market telling us something. This is no longer a fringe target. By 2028 I expect amylin-based therapy to be a standard tier in the obesity treatment algorithm, alongside or layered onto GLP-1s.
Amylin vs Ozempic: How Do They Actually Compare?
Where Amylin Analogs Look Better
-
Side-effect profile: Less nausea, less vomiting, less GI distress at comparable weight-loss endpoints.
-
Muscle preservation: Early signals — particularly with cagrilintide — suggest better preservation of lean body mass.
-
Mechanistic complementarity: Amylin acts on different receptors than GLP-1, making combination therapy additive, not redundant.
Where GLP-1s Still Lead (For Now)
-
Track record: Years of real-world data including cardiovascular and renal outcomes.
-
Monotherapy weight loss in head-to-head settings: Tirzepatide remains the single most potent monotherapy, with up to 22.5% in SURMOUNT-1.
-
Established access and insurance coverage.
The Honest Bottom Line
Amylin analogs are unlikely to replace GLP-1s. The strongest data point — and the most likely future of the field — is combination. CagriSema is a glimpse of what comes next: a GLP-1 backbone plus an amylin analog, hitting two complementary brain pathways at once, with better tolerability than maxing out either drug alone.
When Will Amylin Drugs Be Available?
-
2026: CagriSema (Novo Nordisk) — likely FDA approval and launch this year, pending review.
-
2026–2027: Phase 2 readouts from Roche (petrelintide), Pfizer (MET-233i), and several smaller programs.
-
2027–2028: Eloralintide (Lilly) Phase 3 readouts and potential filing.
-
2028–2030: Oral amylin agonists and selective DACRAs reach late-stage trials. Expect the first oral once-daily amylin pill in this window.
Dr. Vidali notes: Patients ask me every week whether they should wait for the next drug. My answer is always the same: do not delay treatment that is available now in the hope of something better in three years. But if you are already on a GLP-1 and plateauing, or struggling with nausea, the amylin wave will give us real options very soon. Within 24 months, the conversation in my office will look completely different.
What This Means for Patients and Clinicians
-
The era of single-mechanism obesity treatment is ending. Combination therapy targeting GLP-1 + amylin (and eventually + glucagon, + GIP, + PYY) is the future.
-
Tolerability matters as much as efficacy. A drug producing 20% weight loss is useless if a patient stops taking it at month four because of unrelenting nausea.
-
The pancreas is not just an insulin factory. Amylin’s resurrection should remind us that beta-cell biology is rich, multidimensional, and still incompletely mapped.
Frequently Asked Questions
-
Is amylin the same as Ozempic? No. Ozempic (semaglutide) is a GLP-1 receptor agonist. Amylin is a separate hormone that acts on different receptors. The two mechanisms are complementary, which is why combination drugs like CagriSema are so promising.
-
Is amylin safe? The synthetic analog pramlintide has been on the market since 2005 with a well-characterized safety profile. The newer long-acting analogs (cagrilintide, eloralintide, petrelintide) have shown favorable safety in Phase 2 and Phase 3 trials, with notably less GI distress than GLP-1s. Cardiovascular outcome data are still being gathered.
-
Will amylin drugs replace Ozempic and Wegovy? Unlikely. The strongest data point to combination therapy. Expect amylin analogs to be added to GLP-1s, not to replace them.
-
How soon can I get an amylin drug? The first, CagriSema, is expected on the U.S. market in 2026. Most other amylin analogs are 2 to 4 years away.
References
-
Cooper GJ, Willis AC, Clark A, Turner RC, Sim RB, Reid KB. Purification and characterization of a peptide from amyloid-rich pancreases of type 2 diabetic patients. Proc Natl Acad Sci USA. 1987.
-
Westermark P, Wernstedt C, Wilander E, Hayden DW, O’Brien TD, Johnson KH. Amyloid fibrils in human insulinoma and islets of Langerhans of the diabetic cat are derived from a neuropeptide-like protein also present in normal islet cells. Proc Natl Acad Sci USA. 1987.
-
Ryan GJ, Jobe LJ, Martin R. Pramlintide in the treatment of type 1 and type 2 diabetes mellitus. Clin Ther. 2005.
-
Garvey WT, Blüher M, Osorto Contreras CK, et al. Coadministered cagrilintide and semaglutide in adults with overweight or obesity (REDEFINE 1). N Engl J Med. 2025.
-
Billings LK, Hsia S, Bays H, et al. Eloralintide, a selective amylin receptor agonist for the treatment of obesity: a 48-week phase 2, multicentre, double-blind, randomised, placebo-controlled trial. Lancet. 2025.
-
Gostynska SE, Pioszak AA. Amylin receptor subunit interactions are modulated by agonists and determine signaling. Sci Signal. 2025.
-
Lutz TA. Amylin and other peptides involved in appetite control: clinical and pharmacological perspectives. Mol Metab. 2022.
-
Jastreboff AM, Aronne LJ, Ahmad NN, et al. Tirzepatide once weekly for the treatment of obesity (SURMOUNT-1). N Engl J Med. 2022.
-
Wilding JPH, Batterham RL, Calanna S, et al. Once-weekly semaglutide in adults with overweight or obesity (STEP 1). N Engl J Med. 2021.
-
Amylin Pharmaceuticals & Takeda. Discontinuation of pramlintide/metreleptin development for obesity (press release). August 4, 2011.
-
Kruse T, Hansen JL, Dahl K, et al. Development of cagrilintide, a long-acting amylin analog. J Med Chem. 2021.
-
BioSpace. Obesity Space Abuzz With Oral, Amylin Assets as Momentum Rides Into 2026. February 6, 2026.
About the Author: Andrea Vidali, MD writes on endocrine biology, reproductive endocrinology, and emerging metabolic therapeutics for InternationalEndo.com. This article is for educational purposes only and does not constitute medical advice.


